All published articles of this journal are available on ScienceDirect.

The Role of Wharton’s Jelly Secretome in Promoting Dentin-pulp Complex Regeneration — An In Vitro Study on Human Dental Pulp Stem Cells
 iD
Fitri Yuli Mardiyati1
Arini Fitria1
Anggraini Margono1
iD
Lilis Jamilah1
Ike Dwi Maharti1
iD
Shalina Ricardo1
iD
Sylva Dinie Alinda1
iD
Valeria Widita Wairooy1
iD
Romilda Rosseti1
iD
Authors Info & Affiliations
Abstract
Introduction
Regeneration of the dentin–pulp complex is hindered by its low-compliance anatomy. Wharton’s Jelly Secretome (WJS) offers a cell-free, minimally immunogenic approach with potential regenerative benefits.
Materials and Methods
Human dental pulp stem cells (hDPSCs; P3–P4) were cultured under osteogenic, angiogenic, or inflammatory (LPS-treated) conditions. WJS (12.5%, 25%, 50%) was applied. TNF-α, VEGF-A, and DSPP levels were quantified by ELISA. Mineralization in osteogenic cultures was assessed by Alizarin red staining at 21 days. The quantitative data were analyzed using one-way ANOVA at a significance level of 95% (p<0.05), followed by LSD post hoc analysis for homogeneous data.
Results
WJS significantly reduced TNF-α (p < 0.05), increased VEGF-A and DSPP expression (p < 0.05), and enhanced mineral deposition in a concentration-dependent manner.
Discussion
WJS attenuated inflammation by reducing TNF-α in all LPS-stimulated hDPSC groups, with the lowest level at 12.5% early on, indicating suppression of a key cytokine involved in irreversible pulpitis. It also supported regeneration by increasing VEGF-A levels, particularly on day 7 (highest at 50%), suggesting enhanced angiogenesis and tissue homeostasis. In parallel, odontogenic/osteogenic differentiation progressed as reflected by increased DSPP (highest at 12.5% on day 7 and peaking at 50% on day 14) and the greatest mineralized nodule formation at 50% by day 21.
Conclusion
WJS demonstrates anti-inflammatory, pro-angiogenic, and pro-odontogenic effects on hDPSCs, supporting dentin–pulp regeneration. These findings position WJS as a promising cell-free therapeutic for regenerative endodontics, warranting further translational studies.
1. INTRODUCTION
Regenerative Endodontic Procedure (REP) uses cell-based or cell-free therapies to restore damaged pulp– dentin structures, with stem cells, scaffolds, and growth factors as key components [1-6]. Cell-based therapy involves direct stem cell transplantation. Still, it carries risks such as immune rejection and limited availability [5, 7-9], while cell-free therapy promotes endogenous stem cell homing and increasingly employs secretome-derived growth factors to stimulate repair via paracrine signaling [10, 11]. Human dental pulp stem cells (hDPSCs) secrete immunomodulatory factors, including TNF-α, TGF-β, IL-6, IL-10, IL-13, IL-29, and growth factors like FGF-2, PDGF, VEGF, and TNF-α, which regulate inflammation, angiogenesis, and regeneration. During pulpal inflammation, bacterial infection and reduced oxygen availability create a hypoxic microenvironment that activates Hypoxia-inducible Factor-1α (HIF-1α), promoting the expression of pro-inflammatory cytokines such as TNF-α and IL-1β. Hypoxia also favors macrophage polarization toward the pro-inflammatory M1 phenotype, further amplifying inflammation. In addition, activated neutrophils generate Reactive Oxygen Species (ROS) to eliminate pathogens; however, excessive ROS accumulation induces oxidative stress, leading to cellular damage and impaired regenerative capacity of the dental pulp [12-18]. VEGF plays a central role in angiogenesis and dentinogenesis, peaking at day 7 before declining [15-21]. At the same time, DSPP serves as a key odontoblastic differentiation marker, peaking at day 14 before cleavage into DSP and DPP [22-24]. Wharton’s Jelly Secretome (WJS), derived from discarded umbilical cords, contains TGF-β, FGF, VEGF, and IGF, regulating cell proliferation, differentiation, and apoptosis [25-30], offering neurogenic, angiogenic, and anti-inflammatory benefits with low immune rejection risk [12, 26, 29]. WJS shows optimal proliferation at 50% concentration [31] and maximal fibroblast proliferation at 12.5% [32].
Despite increasing interest in cell-free regenerative therapies, the dose-dependent effects of WJS on hDPSCs remain poorly understood. In particular, its coordinated effects on inflammation, angiogenesis, and odontogenic differentiation have not been systematically investigated. This study addresses these gaps by comprehensively determining the concentration-dependent effects of WJS on inflammation, angiogenesis, and odontogenic differentiation in hDPSCs. We hypothesized that WJS would promote these regenerative processes in a dose-dependent manner and that a specific concentration would maximize the response.
2. MATERIALS AND METHODS
This study was approved by the Ethics Committee, Faculty of Dentistry, Universitas Indonesia (No. 10/Ethical Approval/FKGUI/II/2024, Protocol 050080124; No.9/10/ Ethical Approval/FKGUI/II/2024, Protocol 051291223; No.12//Ethical Approval/FKGUI/II/2024, Protocol 050020 124). hDPSCs were previously cultured and stored at the Prodia Stem Cell Laboratory, Jakarta, in collaboration with the Conservative Dentistry Department, Faculty of Dentistry, UI (the cryopreserved cells used in the present study were derived from previously collected samples with Informed consent prior to sample collection).
2.1. Wharton’s Jelly Secretome (WJS)
The UC-MSC-derived secretome (USEPro®, PRODIA Stem Cell) was obtained from the Prodia Stem Cell Laboratory (PROSTEM) and was accompanied by a certificate of analysis. USEPro® is formulated in Dulbecco’s Modified Eagle Medium (DMEM) supplemented with human platelet lysate processed with pharmaceutical-grade heparin and contains several bioactive factors, including BDNF, SDF-1, VEGF, PDGF, EGF, NGF, and FGF. The product used in this study was from batch/lot number UCD18110105 230912B. Each batch undergoes standardized quality-control testing to ensure product quality and consistency. WJS was diluted using Dulbecco’s Modified Eagle Medium (DMEM; Thermo Fisher Scientific Inc., MA, USA) to final concentrations of 12.5%, 25%, and 50%.
2.2. Human Dental Pulp Stem Cells
The hDPSCs used in this study were cryopreserved from a previous study and cultured at the Prodia Stem Cell Laboratory in Jakarta, Indonesia, following established protocols. After 24 h of serum starvation and upon reaching 80% confluence, cells at passages 3–4 were expanded and allocated into one negative control group and three experimental groups: hDPSCs + LPS stimulation (hDPSCs-LPS), hDPSCs + angiogenic medium (hDPSCs-Ang), and hDPSCs + osteogenic medium (hDPSCs-Os) (Table 1). The hDPSCs-LPS group was stimulated with 0.5 μg/mL E. coli LPS for up to 4 hours. The Angiogenic medium for the hDPSCs-Ang group was LonzaTM CC-3156 (LonzaTM Endothelial Basal Medium-2), and the osteogenic medium for the hDPSCs-Os group was (DMEM, 50 μg/mL asam L-askorbat 2-fosfat, 10 mM garam natrium β-gliserofosfat, 10 nM deksametason). Each experimental group was further subdivided into four treatment groups receiving 0% (1000 μL DMEM), 12,5% (125 μL WJS in 875 μL DMEM), 25% (250 μL WJS in 750 μL DMEM), and 50% WJS (500 μL WJS in 500 μL DMEM), 5 × 10⁵ cells were seeded per well in six-well plates and cultured in complete medium until approximately 70% confluence was reached. The cells were then incubated at 37°C in a humidified atmosphere containing 5% CO2 for 24 hours. (Table 1). All groups were prepared in biological triplicate in three independent experiments, and the experiment was performed twice, in accordance with ISO 10993-5.
| Experimental Group | Base Culture Condition | WJS (%) |
|---|---|---|
| Negative control | hDPSCs cultured in DMEM | – |
| hDPSCs-LPS | hDPSCs + 0.5 μg/mL E. coli LPS | 0, 12.5, 25, 50 |
| hDPSCs-Ang | hDPSCs + angiogenic medium | 0, 12.5, 25, 50 |
| hDPSCs-Os | hDPSCs + osteogenic medium | 0, 12.5, 25, 50 |
2.3. TNF-α, VEGF-A, and DSPP Expression
hDPSCs-LPS were cultured in 96-well plates (Table 1) and incubated at 37 °C with 5% CO2. TNF-α was quantified at 48 and 72 h using ELISA (Wuhan Fine Biotech Co., Ltd; range: 15.625–1000 pg/ml; sensitivity: 9.375 pg/ml) with absorbance at 405 nm. VEGF-A was measured on days 3 and 7 in hDPSCs cultured in angiogenic medium, and DSPP on days 7 and 14 in hDPSCs grown in osteogenic medium containing DMEM, 50 µg/ml L-ascorbic acid 2-phosphate, 10 mM β-glycerophosphate, 10 nM dexamethasone, and antibiotics. ELISA detection ranges/ sensitivities were 31.25–2000 pg/ml and 18.75 pg/ml for VEGF-A, and 0.313–20 ng/ml and 0.188 ng/ml for DSPP, with absorbance at 450 or 492 nm.
2.4. Mineral Deposition with Alizarin Red
Cells were seeded in six-well plates (Costar, Cambridge, MA, USA) at an initial density of 5 × 10⁴ cells per well and cultured in TGC-CM or regular DMEM/F-12. The cells were washed twice with Phosphate-Buffered Saline (PBS) and fixed with 95% ethanol for 30 minutes at room temperature. The fixative was carefully removed, and the cells were gently washed three times with distilled water. The cells were then stained with 0.1% Alizarin Red S (Sigma-Aldrich) at 37°C for 30 minutes. Alizarin Red S staining was evaluated by the presence of red deposits or precipitates, indicating mineralization. The formation and distribution of mineralized deposits were visually assessed using a microscope (Axio Observer, Zeiss, Germany). Alizarin Red S staining was used to evaluate the formation of mineralization nodules.
2.5. Statistical Analysis
Quantitative data were analyzed by comparing hDPSC counts between control and treatment groups, with normality and homogeneity assessed using the Shapiro–Wilk test (p > 0.05, n < 50). Normally distributed data underwent one-way ANOVA (p < 0.05, 95% CI), followed by LSD post hoc analysis (p ≥ 0.05) for homogeneous data. Graphs were generated using GraphPad Prism v10.3.1, with significance set at p < 0.05 (*) and p < 0.01 (**).
3. RESULTS
The expression of stem cell markers of Mesenchymal Stem Cells (MSCs) from hDPSCs used in this study was cocktail positive 96.5% CD90+; 90.3% CD105+; and 99.4% CD73+(> 75%) and cocktail negative 0.1% for LinNeg (<2%) (Fig. 1). On the other hand, (Fig. 2) presents the qualitative observations for the hDPSC-LPS groups. Treatment with 0.5 µg/mL E. coli LPS for 24 hours reduced hDPSC size and number (Fig. 2C) compared to untreated controls at 48 and 72 hours (Fig. 1A–B). Cells cultured with 12.5% WJS showed recovery in morphology and number after 24 hours (Fig. 2D), while the 25% and 50% WJS groups exhibited only limited improvements in cell morphology (Fig. 1E–F). Although all USEPro-treated groups showed increased cell numbers, only the 12.5% group closely resembled the control in morphology.
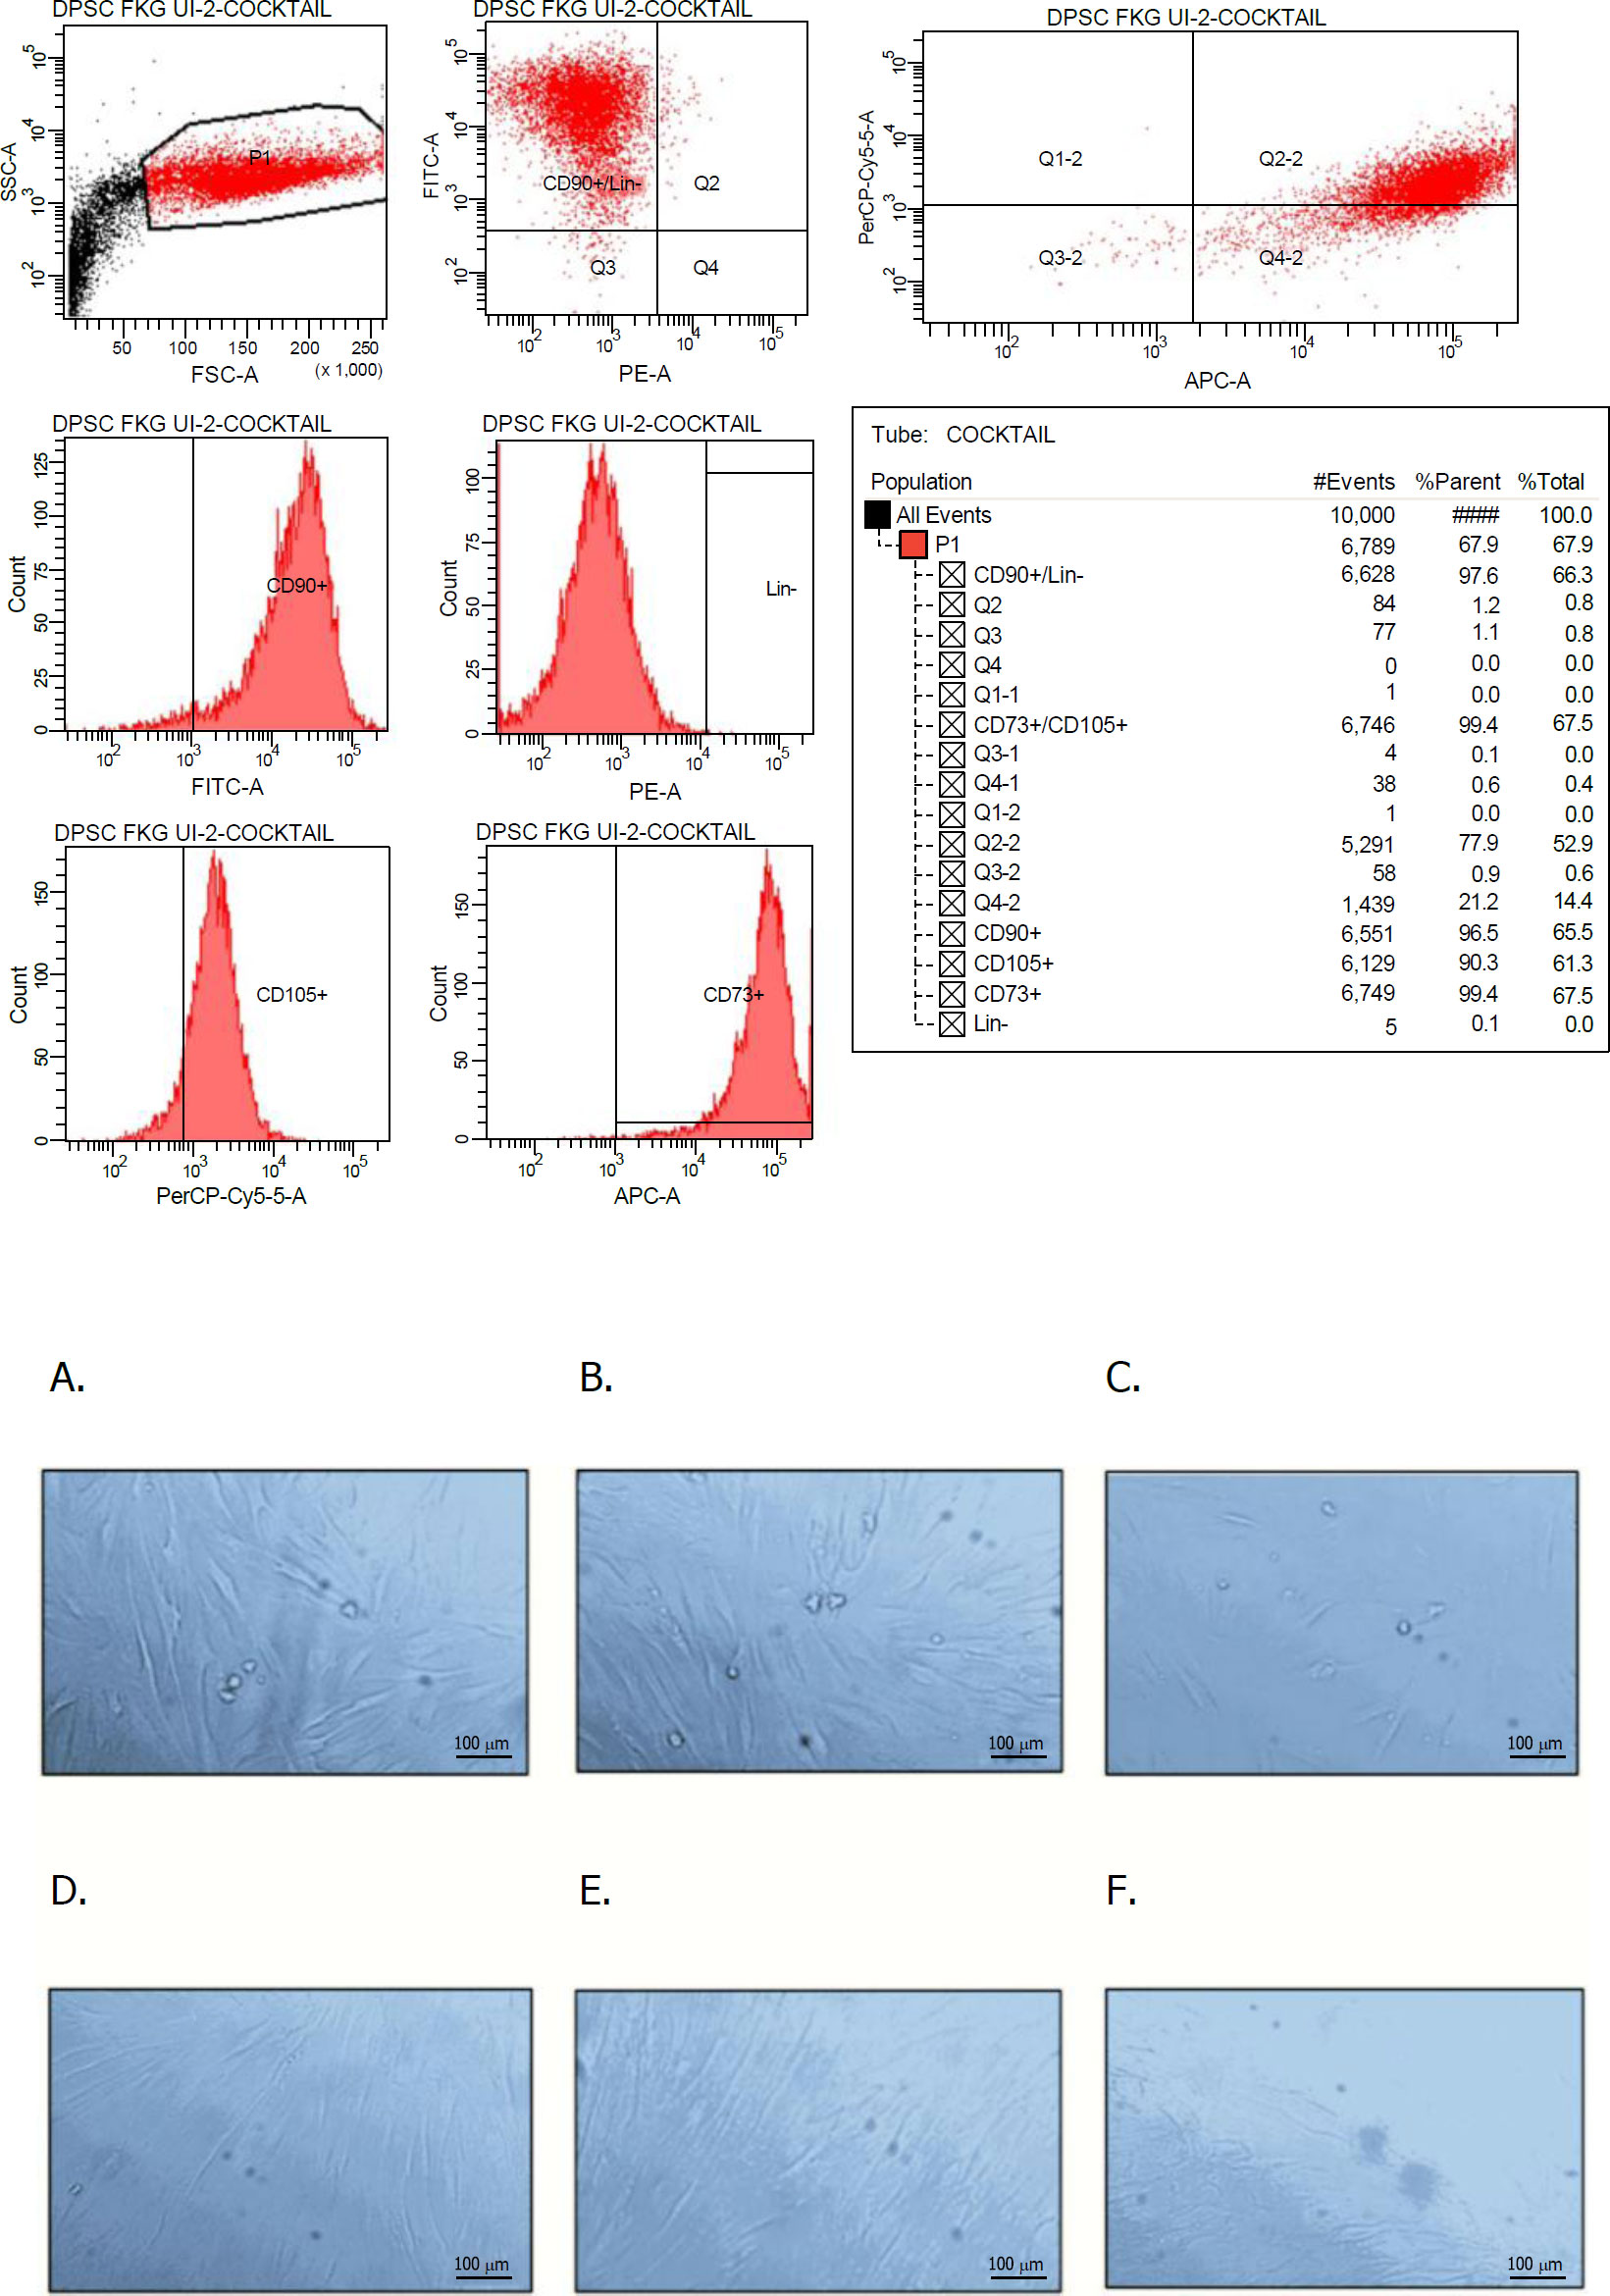
The expression of stem cell markers of hDPSCs from flow cytometry test result; and Qualitative images of hDPSCs-LPS group, from: A.) hDPSCs after 48 hours without LPS treatment; B.) hDPSCs after 72 hours without LPS treatment; C.) hDPSCs 24 hours after LPS treatment (hDPSCs-LPS); D.) hDPSCs-LPS cultured in DMEM and supplemented with USEPro 12.5%; E.) hDPSCs-LPS cultured in DMEM and supplemented with USEPro 25%; and F.) hDPSCs-LPS cultured in DMEM and supplemented with USEPro 50%.
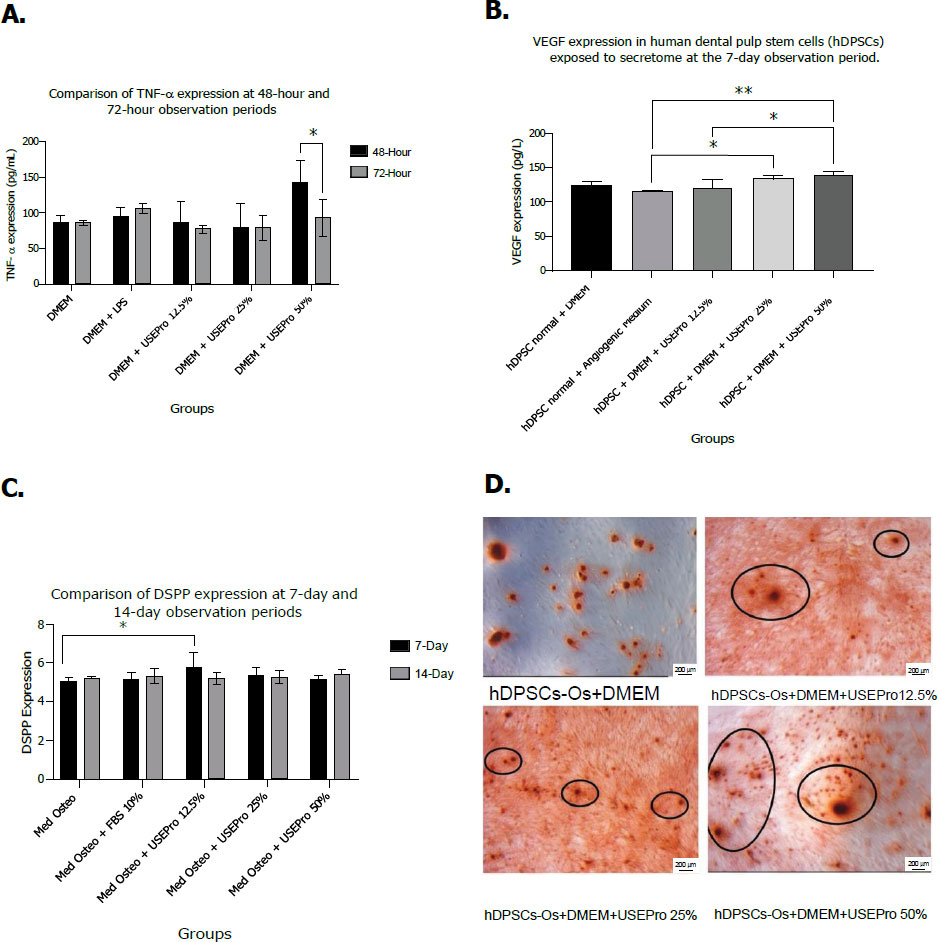
The Statistical analysis of TNF-α expression with p<0.05 (*) after 48 and 72 hours of evaluation (A), and the Statistical analysis of VEGF-A expression in hDPSCs (normal) and hDPSCs normal and angiogenic medium (hDPSCs-Ang) as control groups and USEPro groups (12.5%, 25%, and 25%) after 7 days of evaluation. There was a significant difference between control and experimental groups (USEPro) (*; p<0.0%), also between different concentrations of USEPro groups (experimental) (**; p<0.01) (B), and the Statistical analysis of DSPP expression (Med Osteto=hDPSC-Os) (C), which is in line with the alizarin Red Staining result of all groups; control group, USEPro 12.5%; 25%; and 50% groups on hDPSCs-Os after 21 days of evaluations (D).
3.1. TNF-α, VEGF-A, and DSPP Expression
TNF-α expression (pg/mL) decreased in all hDPSCs-LPS groups treated with WJS (12.5%, 25%, 50%) compared to the positive control, with the lowest levels at 12.5% and 25% (Fig. 2A). After 72 h, the 50% group showed a significant reduction (p < 0.05) (Fig. 2A), indicating all concentrations similarly lowered TNF-α within 72 h. VEGF-A expression showed no significant change at day 3 (Fig. 2B), but by day 7 was significantly higher in the 25% and 50% groups versus the positive control (p < 0.05) and between certain WJS Groups (p < 0.01) (Fig. 2B). DSPP expression varied with time and concentration: on day 7, the highest mean was in the 12.5% group, whereas on day 14, the 50% group showed the highest level (Fig. 2C).
3.2. Mineralization Deposit with Alizarin Red
On day 21, the expression of DSPP, an odontoblast differentiation marker, was confirmed by the formation of mineralized nodules. This was evident from Alizarin Red staining, which highlighted red Ca2+-chelate deposits. Previous research has established DSPP as a late-stage marker for osteogenic and odontogenic differentiation in Dental Pulp Stem Cells (DPSCs), detectable by day 21. All groups treated with WJS demonstrated mineralization compared with the control group, with the 50% WJS group showing the densest and most abundant mineralized nodules. (Fig. 2D).
4. DISCUSSION
Wharton’s Jelly Secretome (WJS) modulates immune and inflammatory responses by releasing soluble factors that suppress lymphocytes, dendritic cells, NK cells, and macrophages; inhibit DC differentiation and MHC-II expression; reduce proinflammatory cytokines such as TNF-α; and promote M2 macrophage polarization by inhibiting the TLR4/MyD88/NF-κB pathway. These effects occur early in inflammation, with TNF-α as a key marker within 24–48 h. In this study, TNF-α levels (pg/mL) were reduced in all WJS-treated hDPSCs-LPS groups (12.5%, 25%, 50%) compared to the control, with the lowest expression across 12.5% and similar suppression at all concentrations after 72 h (Fig. 2A). During pulpal inflammation, activated immune cells generate excessive ROS, inducing oxidative stress and activating the TLR4/NF-κB signaling pathway, thereby increasing TNF-α production. In turn, TNF-α further promotes ROS generation through mitochondrial dysfunction, creating a positive feedback loop that perpetuates inflammation and tissue injury. Consistent with this mechanism, WJS significantly reduced TNF-α levels in LPS-stimulated hDPSCs, suggesting that its immunomodulatory effects may interrupt the ROS–TNF-α inflammatory cycle, thereby attenuating pulpal inflammation [13].
VEGF-A, a key isoform of the VEGF family, plays a central role in angiogenesis during tertiary dentin formation by promoting endothelial cell migration, proliferation, and indirectly stimulating osteogenesis via paracrine regulation of osteogenic growth factors, with signaling mediated through Ras/MAPK, FAK/paxillin, PI3K/AKT, and PLCγ pathways [14, 21, 22]. In this study, VEGF-A expression showed no significant difference at day 3, yet treatment groups exhibited a notable increase versus control (Fig. 2B). The elevated expression in the negative control likely reflected hypoxia-induced oxidative stress, which transiently upregulates VEGF as an early angiogenic response essential for pulp regeneration and homeostasis [3, 21-24]. In the positive control, the angiogenic medium likely enhanced VEGF-A expression by promoting cellular proliferation and differentiation (Fig. 2B). This finding is consistent with a previous study reporting that VEGF-A expression increases during the early stages of wound healing, with upregulation around day initiating neovascularization and reaching a peak within 3-7 days to facilitate oxygen and nutrient delivery for tissue repair [22].
After seven days, VEGF-A expression was significantly higher in the WJS-treated group than in controls (Fig. 2B), demonstrating its potential to promote angiogenesis, modulate inflammation, and support tissue homeostasis through induction of the homeostatic phase, suppression of inflammation, stimulation of proliferation and remodeling, and facilitation of vascular maturation [9, 22, 25]. In vivo, VEGF-A expression begins by day 3, peaks around day 7, and is critical for angiogenesis between days 4–10, coinciding with endothelial migration and vessel formation at injury sites [22]. By day 7, expression typically declines as the inflammatory phase resolves, with early cytokines such as TNF-α, IL-1β, and IL-6 initially driving its upregulation [9]. This decline signals the transition to stable tissue repair, in which maturation replaces active angiogenesis, and internal regulatory mechanisms limit excessive vessel growth.
In connection with the effect of various WJS concentrations, secretome therapy has the potential to decrease TNF-α expression after 48 hours and 72 hours (Fig. 2A). It supports the increase of VEGF-A in 7 days of evaluation (Fig. 2B), so that it can be suggested that USEPro can increase vascularization to areas that require tissue regeneration. VEGF-A can be considered an indicator of secretome quality; if VEGF-A production increases, the secretome has the potential to promote blood vessel formation and regeneration [22].
The highest VEGF-A expression occurred at 50% WJS after 7 days, suggesting this concentration optimally enhances VEGF-A production (Fig. 2B). Higher WJS levels may require longer processing by target cells, aligning with Untoro et al. (2017), who reported 50% WJS achieved the best proliferation via increased TGF-β signaling [30]. VEGF-A, low in early osteoblast differentiation, peaks during terminal differentiation and mineralization, and has been shown by Praja et al. (2022) to promote proliferation, differentiation, mineralization, neovascularization, and reparative dentin formation in vitro and in vivo [24]. Its role in bone remodeling reflects the close interaction between angiogenic and osteogenic factors in bone formation and healing [25], supporting the inclusion of Dentin Sialophosphoprotein (DSPP) as a marker of odontoblast differentiation in this study [30].
DSPP, crucial for dentin mineralization through its components DSP and DPP, is associated with odontoblast activity [27, 28]. In this study, DSPP expression differed significantly between the control hDPSCs-Os and hDPSCs-Os+WJS 12.5% at 7 days, with the highest mean at 12.5% (Fig. 2C), likely due to an optimal balance of growth factors and cytokines for odontoblast differentiation. By day 14, DSPP expression peaked at 50%, reflecting ongoing differentiation and maturation, while at day 21, calcium nodule formation confirmed mineralization, with the greatest deposits in the 50% WJS group (Fig. 2D). This progression indicates that angiogenesis and osteogenesis continued over time, culminating in the formation of fully mature osteoblastic cells after 21 days in osteogenic medium.
Collectively, our findings suggest that WJS exerts multifaceted biological effects by modulating inflammation, promoting angiogenesis, and enhancing odontogenic differentiation. Compared with other cell-free regenerative products, WJS secretome offers several potential advantages. Platelet-derived products such as PRP and PRF provide autologous growth factors but are subject to donor variability and limited standardization. Exosome-based therapies have demonstrated promising regenerative potential; however, their isolation requires specialized equipment, is time-consuming, and often yields limited quantities. In contrast, WJS contains a broad spectrum of soluble cytokines, growth factors, extracellular vesicles, and bioactive proteins that collectively regulate inflammation, angiogenesis, and tissue regeneration. Compared with autologous platelet concentrates and laboratory-prepared conditioned media, a standardized WJS secretome formulation such as USEPro® may offer advantages in manufacturing consistency, storage, scalability, and reproducibility, all of which are important considerations for clinical translation.
Despite these promising findings, several limitations should be considered when interpreting this study's results. An in vitro hDPSC model cannot fully recapitulate the complex microenvironment of the dental pulp, including interactions among stem cells, immune cells, endothelial cells, the extracellular matrix, and bacterial stimuli. In addition, the study evaluated only selected biomarkers associated with inflammation, angiogenesis, and odontogenic differentiation, providing a limited representation of the regenerative process. Future studies should investigate the molecular signalling pathways involved and confirm its regenerative efficacy in three-dimensional culture systems and in vivo models before clinical translation.
CONCLUSION
Wharton’s Jelly secretome (USEPro®) shows significant potential for dentin–pulp regeneration by synergistically driving angiogenesis, modulating inflammation, and inducing odontogenic differentiation, positioning it as a promising cell-free therapeutic strategy in regenerative endodontics. However, further studies using other odontogenic and angiogenic biomarkers are needed to support for its use in regenerative endodontics.
AUTHORS’ CONTRIBUTUIONS
The authors confirm their contributions to the paper as follows: B.D.A., M.A.: Study concept or design; M.F.Y., F.A., J.L.: Data collection; M.F.Y., F.A.: Writing the paper; M.I., A.S., R.S.: Writing–original draft preparation; R.R., W.V: Writing –reviewing and editing. All authors reviewed the results and approved the final version of the manuscript.
LIST OF ABBREVIATIONS
| ANOVA | = Analysis of variance |
| DMEM | = Dulbecco’s Modified Eagle Medium |
| DSPP | = Dentin sialophosphoprotein |
| ELISA | = Enzyme-linked immunosorbent assay |
| hDPSCs | = human dental pulp stem cells |
| LPS | = Lipopolysaccharide |
| LSD | = Least significant difference |
| MSCs | = Mesenchymal stem cells |
| PBS | = Phosphate-buffered saline |
| REP | = Regenerative endodontic procedure |
| ROS | = Reactive oxygen species |
| TNF-α | = Tumor necrosis factor-alpha |
| VEGF-A | = Vascular endothelial growth factor-A |
| WJS | = Wharton’s Jelly Secretome |
ETHICS APPROVAL AND CONSENT TO PARTICIPATE
This research was approved by the Ethics Committee, Faculty of Dentistry, Universitas Indonesia on 13th February 2023 with approval number as follows: No. 10/Ethical Approval/FKGUI/II/2024, Protocol 050080124; No.9/10/Ethical Approval/FKGUI/II/2024, Protocol 051291223; No.12//Ethical Approval/FKGUI/II/2024, Protocol 050020124.
HUMAN AND ANIMAL RIGHTS
All procedures involving human participants were conducted in accordance with the ethical standards of the committee responsible for human experimentation (institutional and national), and with the Helsinki Declaration of 1975, as revised in 2013.
CONSENT FOR PUBLICATION
Informed consent was obtained from all participating adult subjects prior to the study.
AVAILABILITY OF DATA AND MATERIALS
The data sets used during the current study can be provided by the corresponding author (B.D.A.) upon reasonable request.
FUNDING
This study was funded by a grant from the Directorate of Research and Community Engagement at Universitas Indonesia, HIBAH PUTI 2024, with grant number No: NKB-93/UN2.RST/HKP.05.00/2024
ACKNOWLEDGEMENTS
The authors would like to thank Dr. Angliana Chouw, S.Si, M.Farm., Annisa Nur Arofah, S.Si, and Riska Agustina, S.Si from the Prodia Stem Cell Laboratory in Indonesia for their support.

